
Last updated: October 23, 2026
Newborn feeding basics: The Complete Guide starts with one practical truth: a newborn usually needs to eat 8 to 12 times in 24 hours, and the real job is not “getting on a schedule” but learning how to feed on cue, watch the diaper count, and know when a baby needs help. This guide explains what normal feeding looks like, how to choose breast milk or formula, how much to offer, and which warning signs should trigger a call to a pediatrician or lactation consultant.
I write about infant care, feeding systems, and the practical side of early newborn health. Feeding is one of the first places parents get bad advice, because people mix up habits, myths, and one family’s routine with medical guidance. In newborn feeding basics: The Complete Guide, the goal is to keep the baby hydrated, growing, and fed without unsafe pressure on the parent.
Key takeaways
- Newborns usually feed often, in small amounts, and irregularly at first.
- A diaper pattern, weight trend, and alertness matter more than the clock.
- Breastfeeding, pumping, formula feeding, and mixed feeding can all be healthy choices.
- The best feeding method is the one that keeps the baby hydrated, growing, and fed without creating unsafe stress for the parent.
- Jaundice, poor weight gain, very sleepy feeds, and fewer wet diapers are reasons to seek medical advice quickly.
How often should a newborn eat?
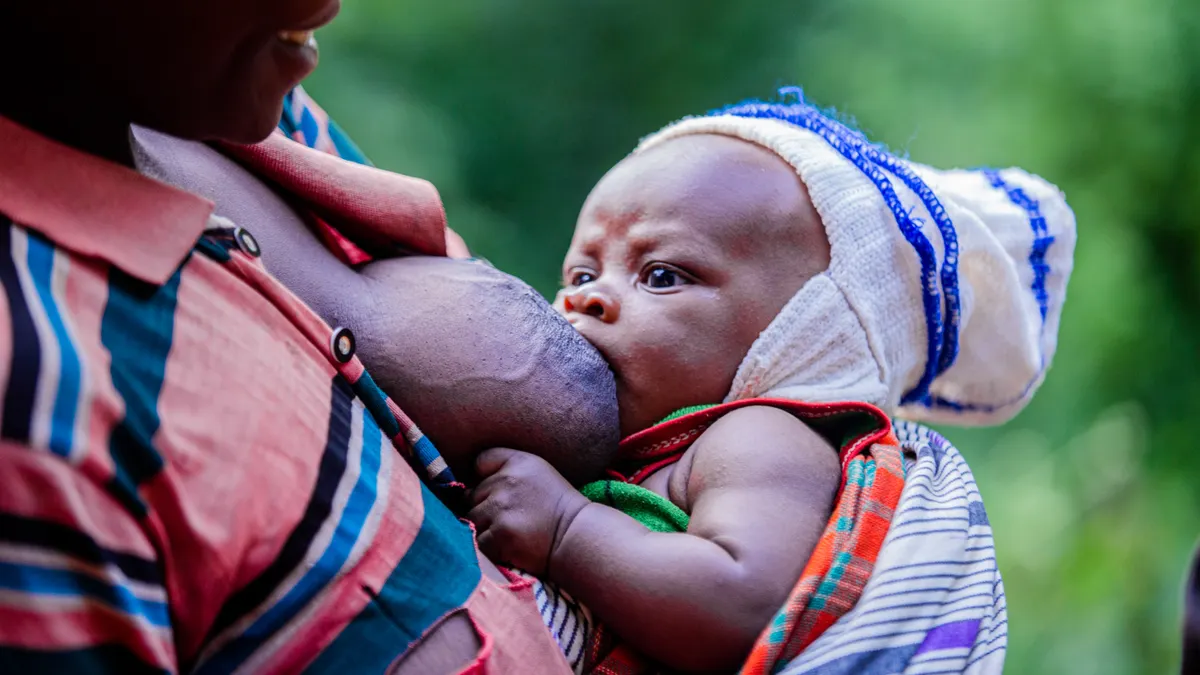
A newborn should usually eat every 2 to 3 hours, or about 8 to 12 times in 24 hours, but some babies cluster-feed and some take slightly longer gaps once feeding is established. That range is a common rule of thumb because the first weeks are about maintaining intake, not spacing meals.
In practice, a newborn may feed for 10 minutes, 20 minutes, or longer, then want to eat again soon after. That can be normal. The pattern looks messy because babies are small, their stomach capacity is limited, and their feeding skill is still developing. A baby who feeds every hour for part of the day is not automatically a problem. A baby who is hard to wake for feeds, however, deserves attention.
The baby’s age matters. In the first days after birth, feeding is often frequent and inefficient. By the end of the first couple of weeks, feeding should usually become more purposeful, even if it is still frequent. The clock alone is not enough. A baby who is feeding frequently but still has too few wet diapers, poor weight gain, or a weak latch needs help sooner rather than later.
A useful mental model is simple: feed often, watch output, and follow the baby’s cues. If the baby is sleepy or jaundiced, a pediatrician may recommend waking for feeds. If the baby is term, otherwise well, and gaining appropriately, the feeding rhythm can be more flexible.
For a parent who wants one plain answer: do not wait for a strict schedule in the first weeks. Feed when the baby shows hunger cues, and if those cues are hard to read, treat waking, rooting, hand-to-mouth motions, and fussiness as signs to offer a feed. If you are unsure, consult a pediatrician, midwife, or lactation consultant. The American Academy of Pediatrics explains early hunger cues and newborn feeding patterns in its infant feeding guidance: https://www.aap.org/
Breast milk or formula: what actually changes?
Both breast milk and infant formula can support healthy growth, but they differ in logistics, flexibility, and the kind of work they ask of the parent. The right choice is the one that is sustainable, safe, and compatible with the family’s realities.
Breast milk has major advantages for some families. It is made for human infants, changes over time, and can be given directly at the breast or expressed into a bottle. The biggest practical strength is adaptability: a baby can feed at the breast without mixing, sterilizing, or measuring. That can be especially useful in the early weeks, when feeding is frequent and night wakings are common.
Breastfeeding is not effortless, though. It can be painful if latch is poor, exhausting when feeds are long or frequent, and emotionally heavy when supply, tongue-tie concerns, or nipple damage enter the picture. Some mothers need hands-on help from an International Board Certified Lactation Consultant (IBCLC), and some need medical evaluation if the baby is not transferring milk well. Breastfeeding is also not the right answer if the parent is taking a medication incompatible with breastfeeding, has a medical contraindication, or simply cannot make the system work without serious harm.
Formula has its own strengths. It allows anyone to feed the baby, which matters in families with shared caregiving, after cesarean recovery, during illness, or when the parent’s milk supply is low. It gives more visibility into how much the baby is taking at a given feed, and that can lower anxiety for some parents. It is also a legitimate, healthy option; formula-fed babies are not “failed” babies.
The trade-offs are real. Formula requires mixing, clean bottles, and attention to safe preparation. Once opened, powder and prepared bottles have storage rules, and feeding out of an unclean bottle setup creates avoidable risk. Formula also brings ongoing cost and logistics that breast milk does not. CDC formula preparation and storage guidance is the safest place to check the basics: https://www.cdc.gov/
The best choice depends on three things: whether the baby is feeding well, whether the parent has support, and whether the feeding plan can be sustained for weeks, not days. If breastfeeding is causing worsening pain, exhaustion, or poor intake, a temporary or permanent switch, or a mixed-feeding plan, may be the wiser choice. If formula is the main plan, the key is safe preparation and responsive feeding, not guilt.
Breastfeeding and newborn feeding basics: who should use it, and who should skip it?
Breastfeeding wins when milk transfer is good, the parent wants it, and the family has the time and support to work through the early learning curve. It is often the best fit for families who want direct feeding, lower gear burden, and the option to feed on demand without preparing bottles.
It is not the right fit for everyone. Parents with persistent nipple trauma, unresolved low supply, or a baby who cannot latch well should not be told to “just push through” for weeks. That advice can delay treatment and create a miserable start. Breastfeeding also becomes a poor choice when it is medically contraindicated or when the emotional cost is too high to keep going safely. A baby who is not getting enough milk is never a candidate for “wait and see” just because breastfeeding is preferred in theory. If there is doubt, consult a pediatrician or IBCLC quickly, and use the CDC and AAP feeding guidance as a backup reference point: https://www.cdc.gov/ and https://www.aap.org/
The strongest signal that breastfeeding is working is not a single perfect feed. It is a pattern: the baby seems satisfied after feeds, diaper output is adequate, and weight gain trends in the right direction. A baby who feeds constantly but remains unsatisfied, sleepy, or underfed needs a reassessment. In that situation, a weighted feed, lactation visit, or pediatric exam can uncover the problem faster than more guesswork.
Formula feeding: the specific situations where it wins
Formula wins when reliable intake matters more than method, when the parent cannot or does not want to breastfeed, or when milk supply and transfer are not enough to meet the baby’s needs. It is especially useful when a second caregiver needs to share feeds, when the parent is recovering physically, or when a baby needs a predictable measured bottle intake.
The downside is mostly practical, but practical matters. Formula must be mixed correctly, bottles and nipples must be cleaned properly, and caregivers need to understand hunger cues so the baby is not pressured to finish a bottle just because it is prepared. A bottle can make overfeeding easier if adults confuse “finished the bottle” with “still hungry.” It also creates a supply chain: the right product has to be available, and the family has to keep enough on hand.
For parents who want certainty, formula provides more visible intake than direct breastfeeding. That can be calming, especially in the first two weeks when everyone is trying to figure out whether the baby is getting enough. The downside is that visibility can become anxiety if every ounce gets tracked obsessively. A healthy formula-feeding routine is calm, prepared, and responsive — not rigid.
The honest side-by-side
| Criteria | Breast milk | Formula | Winner for condition |
|---|---|---|---|
| Preparation at 2 a.m. | No mixing if feeding directly at the breast | Requires measuring, mixing, and cleaning | Breast milk when convenience matters most |
| Who can feed the baby | Usually the lactating parent unless milk is expressed | Any trained caregiver | Formula for shared caregiving |
| Visibility of intake | Harder to measure without a weighted feed | Easy to see the bottle volume offered | Formula for parents needing clear numbers |
| Flexibility during supply issues | Depends on milk production and transfer | Less dependent on parental supply | Formula when intake reliability is the priority |
| Need for equipment | May need pump, flange sizing, storage bags, nursing pads | Needs bottles, nipples, formula, and cleaning supplies | Depends on which gear burden is easier to manage |
| Risk of user error | Latching and transfer problems can reduce intake | Mixing and storage errors can create safety issues | Breast milk for those with good support; formula for those comfortable with prep rules |
| Medical compatibility | May be limited by certain medications or conditions | Broadly usable for most healthy infants | Formula when breastfeeding is medically unsuitable |
| Cost over time | Can still involve pump and support costs | Ongoing product cost | Breast milk if direct feeding works and is sustainable |
| Parent energy drain | Often high in the first weeks if feeds are frequent | Can be shared more evenly across caregivers | Formula for protecting sleep and workload balance |
The table does not mean one method is “better” in a moral sense. It means the feeding method should match the family’s real constraints. A parent in pain, a baby with poor transfer, or a household with several caregivers may be better served by formula or mixed feeding than by a strict breastfeeding-only plan. A parent with strong support and good latch may find direct breastfeeding simpler than any bottle setup.
How much should a newborn take at each feeding?

A newborn should take enough to settle, gain weight, and stay hydrated, not a fixed amount that looks neat on a chart. The exact volume varies with age, feeding method, and whether the baby is taking breast milk or formula.
For breastfed babies, intake is harder to quantify because milk transfer happens at the breast. The more useful indicators are swallowing during feeds, satiety afterward, diaper output, and weight checks. A parent may hear “just feed on demand,” which is true but incomplete. Feeding on demand works best when the baby is actually transferring milk well.
For bottle-fed babies, amounts are easier to track. Newborn bottle volumes are usually small and increase as the stomach and feeding skill mature. The important point is not forcing a baby to finish a bottle. If the baby turns away, slows down, or falls asleep, that is usually a cue to stop, burp, and reassess rather than pushing the bottle to empty.
The danger on both sides is underfeeding. A baby who is not getting enough may have fewer wet diapers, persistent hunger after feeds, lethargy, poor latch, or inadequate weight gain. Another danger is overfeeding by bottle, usually when adults interpret rooting or fussing as a need for more milk when the baby may instead need burping, a diaper change, skin-to-skin contact, or sleep.
One practical rule helps: feed the baby, then observe the baby. A satisfied infant should look calmer, relax the hands and face, and give a sense that the feed “took.” A baby who remains frantic, sleepy in an odd way, or unsatisfied after repeated feeds needs a closer look.
What are the signs a newborn is getting enough?
A newborn is probably getting enough when the diaper count rises, the baby feeds actively, and the weight trend is moving the right way. Those three clues matter more than the parent’s anxiety after a single difficult feed.
Wet diapers are one of the best day-to-day signals because they reflect hydration and intake. Stool patterns also change over the first days as meconium transitions to milk stools. By the second week, a baby should usually have a more established pattern, though that pattern varies with feeding type and age. Weight checks remain the gold standard for intake assessment, which is why pediatric follow-up matters. The AAP and CDC both emphasize growth monitoring in early infancy: https://www.aap.org/ and https://www.cdc.gov/
A baby who feeds well can still be underfed if latch is poor or bottle intake is too low. That is why “seems hungry” and “is getting enough” are not the same thing. Some newborns act fussy for reasons unrelated to hunger. Others look sleepy and quiet while actually taking in too little milk. The outer behavior is useful, but not enough on its own.
The red flags are straightforward: too few wet diapers, a very sleepy baby who is hard to wake for feeds, weak sucking, persistent jaundice, dry mouth, sunken soft spot, or poor weight gain. Those signs do not automatically mean an emergency, but they do mean the feeding plan needs review quickly.
Pediatric follow-up in the first days and weeks is not just routine bureaucracy. It is the point at which feeding problems are caught before they become dehydration, severe weight loss, or a deeper medical issue.
How do I know when to wake the baby for a feed?
A baby should be woken for feeds when a clinician has advised it, when the baby is very sleepy, or when the diaper and weight pattern suggest intake may be too low. Newborns are not always reliable at waking themselves, especially in the early days or after a difficult birth.
This is where parents often get conflicting advice. One person says never wake a sleeping baby; another says never let a newborn go longer than 3 hours. The practical answer is in the middle: a healthy, feeding-well baby may gradually tolerate longer gaps, but the first weeks are not the time to experiment. If the baby is premature, jaundiced, small for gestational age, or having feeding issues, waking for feeds is more likely to be necessary.
Waking a baby is usually gentler than parents expect. Light unwrapping, diaper changes, skin-to-skin contact, and offering the breast or bottle when the baby stirs can help. If waking takes a long time or the baby consistently refuses to feed, that is not just “sleepy newborn behavior.” It is a reason to call the doctor or lactation support line. Because of that, a professional should confirm whether the wake-up plan should continue, change, or stop.
The trade-off is real: waking protects intake, but repeated disturbed sleep can exhaust the household. That is why the plan should be tied to the baby’s medical status, not to a one-size-fits-all rule. A baby with stable weight gain may not need the same strict waking schedule as a baby whose intake is borderline.
What feeding problems should make me call for help?
A newborn should be evaluated promptly if feeds are painful, intake seems weak, diaper output is low, jaundice is worsening, or the baby is unusually sleepy. Those are not problems to “watch for a few more days” if they are persistent.
Pain during breastfeeding is not a badge of honor. Sharp nipple pain, cracked skin, blanching, or a pinched nipple shape after feeds can point to poor latch or oral restriction. In that situation, more frequent feeding alone does not solve the problem. The mechanics have to be assessed.
Bottle feeding problems can be quieter but just as important. A baby who coughs, sputters, arches, seems to struggle with flow, or refuses repeated feeds may need nipple flow adjustment or medical evaluation. A parent who finds every bottle feed stressful is also facing a real feeding problem, because the feed has to work for the caregiver too.
Weight loss beyond the expected early newborn pattern, delayed return to birth weight, or a baby who seems more sleepy than awake should prompt a call. So should signs of dehydration, persistent vomiting, or a baby who is difficult to rouse enough to eat.
There is a legitimate boundary here: not every rough feed is a crisis. Many newborns have uneven days, especially during growth spurts or cluster-feeding periods. The point is pattern and persistence. Repeated poor feeds plus weak output is a medical problem, not a parenting flaw. When in doubt, consult a pediatrician, and use trusted guidance from the AAP or NHS newborn feeding advice as a reference point: https://www.aap.org/ and https://www.nhs.uk/
Which feeding plan is right if the first choice is not working?
The right feeding plan is the one that keeps the baby safe and the parent functional, even if that means changing course. Mixed feeding is not a failure; it is often the most practical bridge when the first plan stalls.
A strong breastfeeding start can still need formula supplementation if the baby’s intake is low or weight gain is behind. A formula-feeding family may decide to add pumped milk if supply becomes available. Some families move to full formula after a painful or stressful start. Others keep direct breastfeeding but add bottles at certain times. None of those paths is morally inferior to the others.
The main mistake is staying loyal to a plan that is not working. A feed plan should be judged by outcome, not ideology. If the baby is not gaining, the output is poor, or the parent is breaking down, the plan has failed and needs revision. That revision may be temporary or permanent.
This is also where the right professional support matters. An IBCLC, pediatrician, or postpartum clinician can sort out whether the issue is latch, supply, bottle technique, flow rate, reflux-like symptoms, tongue-tie concerns, or something else. The family should not have to diagnose feeding dysfunction alone.
When to choose breast milk, formula, or mixed feeding
Choose breast milk if the baby latches and transfers well, the parent wants to breastfeed, and the household can support frequent feeds or pumping. Choose formula if direct breastfeeding is not working, if the parent wants a shared-care system, or if safe, consistent intake matters more than feeding method. Choose mixed feeding if the baby needs more intake than breast milk alone is providing, if the family needs flexibility, or if a transition is necessary to protect the parent’s health.
Neither is the right choice if the baby is failing to feed well and the problem is being ignored. That is the disqualifying situation. A feeding plan cannot substitute for medical follow-up.
For authoritative guidance, the American Academy of Pediatrics offers infant feeding guidance, and the CDC’s infant nutrition resources are useful for safety basics around breast milk and formula preparation. The World Health Organization also has infant feeding guidance that helps frame early feeding recommendations in a broader clinical context. Newborn feeding basics: The Complete Guide works best when those sources are used to confirm safety, not to replace local medical advice.
What should a newborn feeding routine actually look like?
A newborn feeding routine should be predictable in purpose, not rigid in timing. The purpose is simple: feed often enough, safely enough, and comfortably enough that the baby stays hydrated and grows.
In a good routine, hunger cues are noticed early, feeds are offered before the baby is frantic, and the caregiver watches for signs of effective sucking, swallowing, and relaxation afterward. Bottles are prepared correctly, stored safely, and not forced. Breastfeeding families get help early if latch hurts or transfer seems weak. Weight checks and diaper counts are tracked without turning the house into a laboratory.
The routine also has to work for the adult. A feeding plan that destroys sleep, creates ongoing pain, or depends on constant heroic effort is not a sustainable newborn plan. That is not a character failure. It is a sign that the feeding method, the support, or the expectations need to change.
What I would tell a parent who is overwhelmed right now
A newborn feeding crisis is usually a system problem, not a personal one. The first job is to make sure the baby is eating often enough, making enough wet diapers, and being followed by a clinician if weight gain or jaundice is a concern.
If breastfeeding hurts badly, if formula preparation feels confusing, or if the baby seems too sleepy to eat, the answer is not to keep guessing for another week. Get help sooner. The earlier the pattern is checked, the easier it is to fix.
The simplest working rule is this: feed the baby, watch the baby, and ask for help when the baby’s behavior, diapers, or weight stop matching what healthy feeding should look like.
Drafted with AI; not yet reviewed by a person.